
Medicaid Reform
WHY STATES ARE ACTING
Taxpayers are spending more on Medicaid prescription drugs, yet less of that funding is reaching the community pharmacies that directly serve patients. When public investment rises but frontline care resources decline, accountability demands action.
State audits of Medicaid managed care pharmacy programs have uncovered:
- Spread pricing and opaque payment flows
- Differential reimbursement practices
- Limited transparency in rebates and administrative fees
- Steering and restrictive network practices
In response, states are advancing structural reforms to strengthen oversight, improve transparency, and protect patient access.
NCPA PRIORITY REFORMS
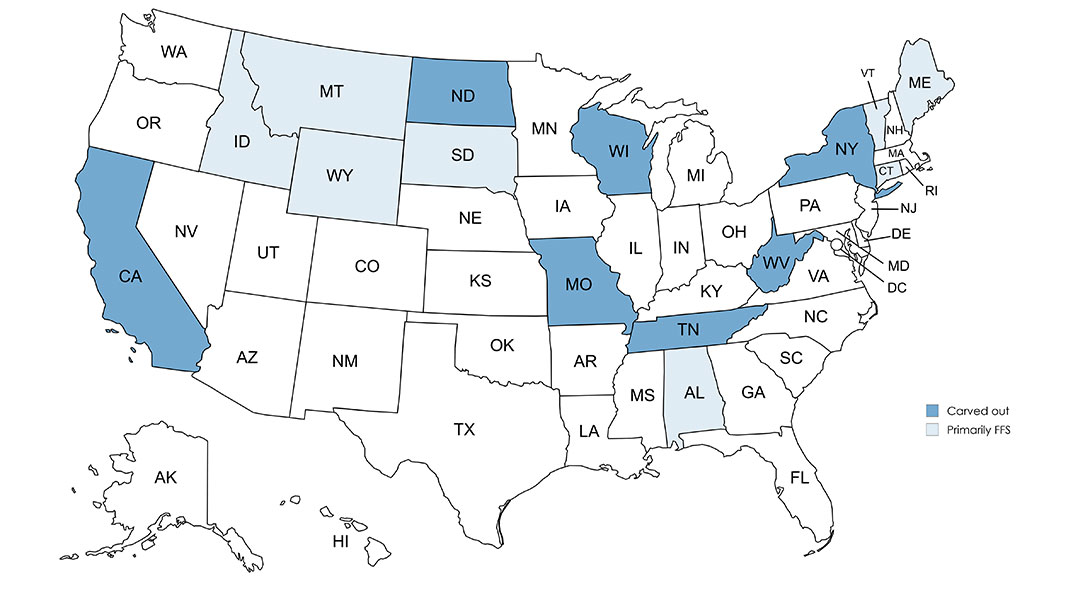
Carve Pharmacy Benefits Out To Fee-for-Service
What This Means
The state administers the pharmacy benefit directly through its Medicaid fee-for-service (FFS) program rather than delegating it to managed care plans. Seven states, including California, Missouri, New York, North Dakota, Tennessee, West Virginia and Wisconsin, have carved out pharmacy benefits from managed care.
Why States Pursue This Approach
- Increases direct state oversight
- Aligns reimbursement methodology statewide
- Enhances transparency in drug pricing and rebate administration
- Simplifies network participation standards
Require Managed Care To
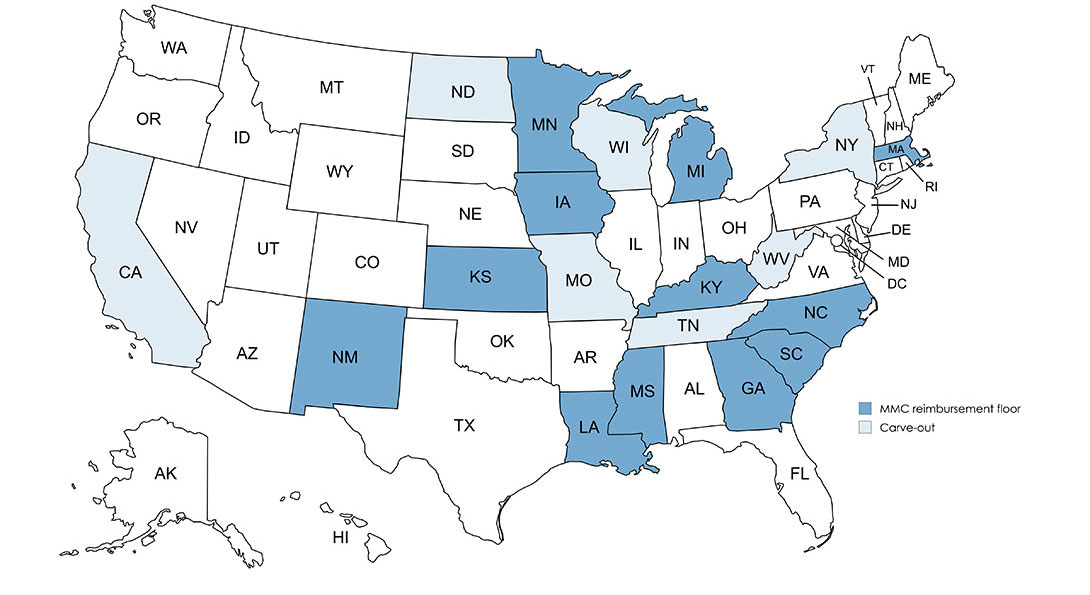
Reimburse at Transparent FFS Rates
What This Means
States require managed care organizations (MCOs) or their contracted PBMs to reimburse pharmacies using the state’s transparent Medicaid fee-for-service methodology (often NADAC-based ingredient cost plus a professional dispensing fee). Twelve states, including Georgia, Iowa, Kansas, Kentucky, Louisiana, Massachusetts, Michigan, Minnesota, Mississippi, New Mexico, North Carolina and South Carolina, have established a Medicaid managed care reimbursement floor.
Why States Pursue This Approach
- Reduces spread pricing risk
- Aligns managed care and FFS reimbursement
- Improves predictability for pharmacies
- Strengthens oversight
Strengthen Managed Care
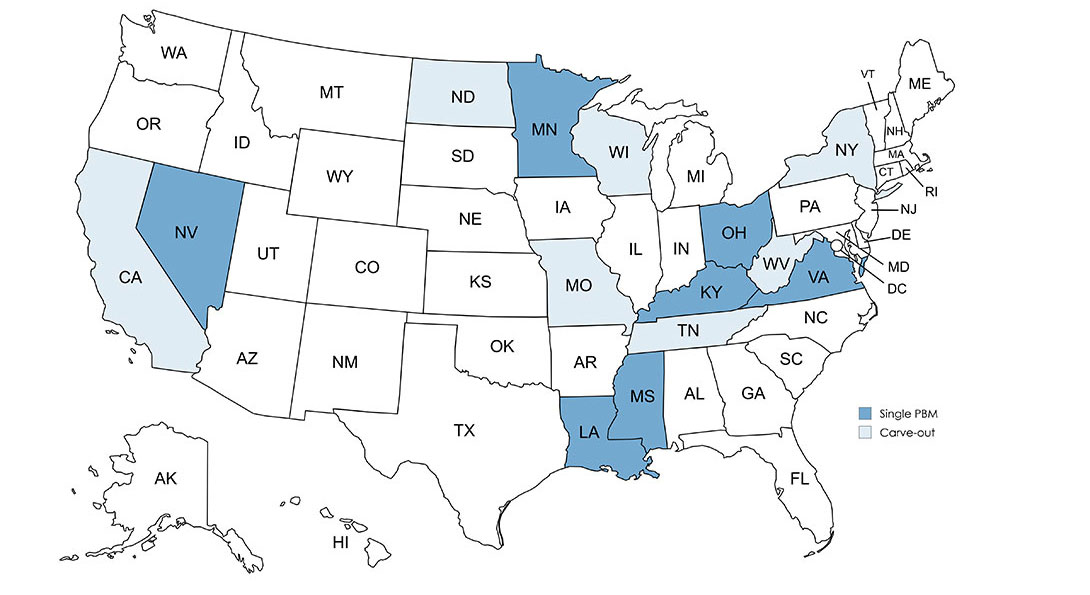
Oversight and Accountability
What This Means
States have adopted additional structural reforms to increase transparency and centralize oversight. One way this has been done is through a single PBM model. Under this model. the state contracts with one PBM to administer Medicaid pharmacy benefits statewide. Seven states, including Kentucky, Louisiana, Minnesota, Mississippi, Nevada, Ohio and Virginia, have transitioned to a single PBM model.
Why States Pursue This Approach
- Enhance accountability for taxpayer-funded spending
- Improve oversight of reimbursement and pricing practices
- Reduce duplicative administrative costs
STATE AUDITS AND INVESTIGATIONS
Multiple state audits and investigations have reviewed Medicaid managed care pharmacy practices and found that an excessive amount of taxpayer dollars remain with PBMs.
- Arkansas: A state-commissioned report found that PBMs in the Medicaid program reimbursed national chain pharmacies more (defined as greater than 5 percent difference) than regional chain and independent pharmacies for the same drug.
- Florida: A report found PBMs steer patients to PBM-affiliated pharmacies, and “when it comes to dispensing brand name drugs, MCO/PBM-affiliated pharmacies are making 18x to 109x more profit over the cost of the drugs than the typical community pharmacy.”
- Illinois: An audit found $200 million of spread pricing in 2021-2022, revealing no monitoring of contracts, including reimbursement rates or rebates, and non-compliance with many statutory requirements.
- Kentucky: In response to a state report that found state PBMs keep $123.5 million in spread annually, the attorney general has launched an investigation into allegations that the PBMs have overcharged the state and discriminated against independent pharmacies.
- Louisiana: PBMs retained $42 million that was incorrectly listed as “medical costs.”
- Maryland: A state Medicaid report found PBMs pocket $72 million annually in spread pricing alone.
- Michigan: Drug price manipulation allowed PBMs to overcharge Michigan Medicaid by at least $64 million.
- New York: An audit found the state unnecessarily paid $605 million to Medicaid MCOs and their PBMs over a four-year period, because “MCOs typically work with their PBMs to conduct their own clinical reviews to identify drugs that provide the greatest value to them and therefore should be placed on the drug formulary."
- Ohio: The state auditor found that, of the $2.5 billion that’s spent annually through PBMs on Medicaid prescription drugs, PBMs pocketed $224.8 million through the spread alone during a one-year period.
- Oregon: A 2023 audit found insufficient transparency and compliance with highly inconsistent reimbursement, including twice as much reimbursement to PBM-owned pharmacies than to independent pharmacies for selected drugs.
- Pennsylvania: In just 4 years, the amount that taxpayers paid to PBMs for Medicaid enrollees more than doubled from $1.41 billion in 2013 to $2.86 billion in 2017.
- Virginia: A state-commissioned report on Medicaid found PBMs pocket $29 million in spread pricing alone.
Frequently Asked Questions About Medicaid Managed Care Pharmacy Reform
-
What is spread pricing in Medicaid managed care?
Spread pricing occurs when a PBM charges a Medicaid managed care plan more for a prescription drug than it reimburses the pharmacy and retains the difference. States have adopted pass-through pricing models or reimbursement alignment policies to address these concerns.
-
What is the difference between pass-through pricing and fee-for-service reimbursement requirements?
Pass-through pricing requires PBMs to pass the full drug ingredient cost and dispensing payment through without retaining spread. Requiring FFS-equivalent reimbursement aligns managed care pharmacy payments with the state’s established Medicaid FFS methodology.
-
What is a pharmacy carve-out?
A pharmacy carve-out occurs when a state removes the prescription drug benefit from managed care and administers it directly through the Medicaid FFS program.
-
What is a single PBM model?
Under a single PBM model, the state contracts with one PBM to administer pharmacy benefits statewide instead of allowing each MCO to contract separately.
-
Why are states adopting a single preferred drug list?
A single preferred drug list promotes consistency across plans, improves administrative simplicity, and strengthens state oversight of formulary decisions.
-
How has NCPA supported states in their Medicaid reform efforts?
- Supporting Pennsylvania's Proposed Single PBM (2026)
- Supporting Maryland's Proposed Medicaid Cost of Dispensing Bill (2026)
- Supporting Maryland's Proposed Single PBM (2026)
- Supporting Virginia's Proposed Single PBM (2025)
- Supporting Nevada's Proposed Single PBM - SB 149/SB 389 (2025)
- Supporting Rhode Island's Prohibition of Spread Pricing - HB 5498 (2025)
- Supporting Indiana's Proposed Single PBM - SB 503 (2025)
- Supporting Utah's Proposed Medicaid Pharmacy Carve-Out - HB 409 (2025)
- Supporting Maryland's Proposed Reimbursement Floor - SB 438 (2025)